Say “hip dysplasia”, and most people think of babies. That’s the usual story – it gets picked up early. Yet a fair number of Australian adults carry it too, and some go years without knowing. The diagnosis might land after a long stretch of hip pain or stiffness that never had a clear reason behind it. Or it turns up only when things get bad enough that you can’t brush them off anymore. If you’ve just been diagnosed, chances are one question is already circling: will you need surgery? It depends, and that’s the honest version.
When Conservative Treatment May Be Sufficient
Not everyone ends up in an operating theatre. When the case is mild, and there’s little damage to the joint, non-surgical care often does the job.
Physical therapy and structured exercise
A physiotherapy plan shaped around your hip builds up the muscles that keep the joint steady. More stability, less discomfort. And if you keep at it, symptoms tend to ease off gradually rather than tighten their grip.
Weight management and lifestyle changes
Extra weight leans hard on a joint that’s already struggling. Nobody’s asking for a total overhaul, though. Trim even a little, and you take pressure off, cut the pain, and make ordinary movement less of a chore.
Pain management and anti-inflammatory strategies
There’s a decent toolkit here: over-the-counter anti-inflammatories, corticosteroid injections, small changes to how you go about your day. None of it repairs the underlying structure. What it does is make the weeks and months ahead more bearable, and that matters more than it might sound.
Monitoring and regular check-ups
If your symptoms are stable, your doctor may simply want to watch. That means occasional scans and reviews to see whether anything shifts. It feels like doing nothing, but keeping tabs is the sensible move when the joint isn’t sliding downhill.
Indicators That Surgery May Be Recommended
There’s a ceiling to what conservative care can achieve. When symptoms climb, or the imaging reveals genuine structural problems, your orthopaedic specialist may start talking about an operation. Here’s what usually prompts that shift.
Persistent pain that doesn’t respond to conservative treatment
Pain that keeps wrecking your sleep, your work, or the basics of getting around – even after months of physio and medication – tends to mean the joint needs fixing rather than calming.
Progressive joint damage on imaging
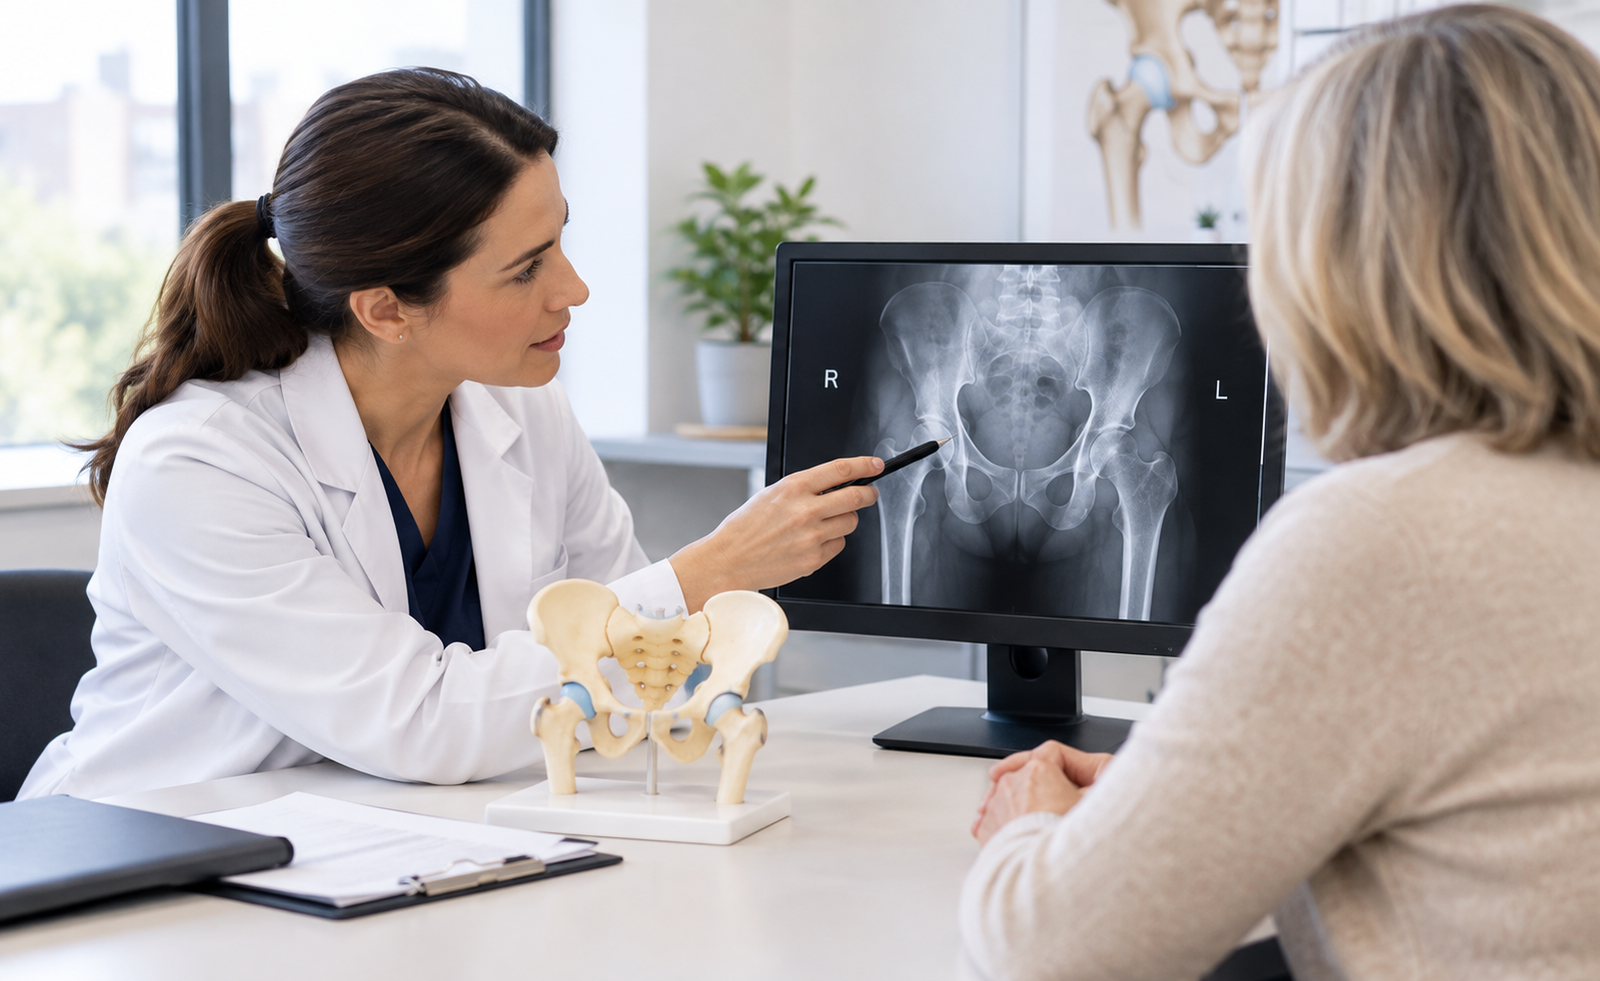
X-rays and MRIs catch cartilage wear, bone changes, and other slow decline. Once the scans show the joint getting worse instead of holding its ground, surgery becomes harder to put off.
Functional limitations affecting daily life
Struggling to walk, dreading a flight of stairs, an ache that creeps in after too long in a chair – all of it signals that dysplasia is chipping away at your quality of life. When conservative care can’t turn that around, surgery for hip dysplasia may give you something that actually lasts.
Risk of early-onset osteoarthritis
Ignored, hip dysplasia can hasten cartilage breakdown and drag osteoarthritis in years ahead of schedule. In some cases, a surgeon will step in for that exact reason: to guard the joint and keep arthritis at bay.
Structural instability or labral tears
The labrum is the cartilage ring around your hip socket, and a dysplastic joint puts it at risk. Tears there bring pain and instability that rarely sort themselves out. They usually call for surgical repair, handled at the same time as the dysplasia.
The Right Time to Act
This isn’t a condition that sits still. Wait too long and your choices narrow while recovery gets messier. Acting early is about protecting your own joint for as long as it’ll last – and, with luck, delaying a hip replacement or dodging one altogether.
So if the pain won’t quit, or you’re staring at a fresh diagnosis, find an orthopaedic specialist who really knows adult hip dysplasia. A single well-timed conversation can shape how you move and feel for years!